

What is spinal stenosis?
Spinal stenosis means the spaces inside your spine have narrowed. This can squeeze the spinal cord or the nerves that branch off it. It happens most often in the lower back (lumbar) and the neck (cervical).
What causes it?
The most common cause is age-related wear and tear, often called arthritis of the spine. Over time:
- Discs lose water and shrink, so the spine settles
- Facet joints wear down and form bone spurs
- Ligaments thicken
Together, these crowd the nerves. By age 50, up to 95% of people show some wear-and-tear changes on imaging, though many never have symptoms. Stenosis is most common after 60. Less often, people are born with a narrow canal, or stenosis follows an injury, a slipped vertebra (spondylolisthesis) or other conditions.
What does spinal stenosis feel like?
In the lower back, common signs are:
- Aching or burning pain in the buttocks that spreads down one or both legs
- Numbness, tingling or cramping in the legs or feet
- Legs that feel heavy or weak when you walk
- Symptoms that get worse when standing or walking and better when sitting or bending forward
In the neck, stenosis can cause neck pain, numbness or tingling in the arms and hands, or hand weakness and clumsiness.
Why does leaning forward help?
Bending forward opens up the back of the spinal canal, giving nerves a little more room. That is why many people with stenosis can walk farther while leaning on a shopping cart or can ride a stationary bike comfortably, but struggle to walk 1 or 2 blocks upright.
How is it diagnosed?
Your doctor will ask about your symptoms and examine your strength, reflexes and sensation. Imaging may include:
- X-ray to show bone spurs, disc height loss or a slipped vertebra
- MRI to show the discs, ligaments and nerves
- CT or CT myelogram if you can’t have an MRI
- EMG and nerve conduction studies to check whether nerves are being affected, or whether another problem such as neuropathy is the cause
What are the nonsurgical treatment options?
| Treatment | What it does | What to know |
|---|---|---|
| Physical therapy | Builds core strength, flexibility and walking tolerance | The foundation of care; benefits build over weeks |
| Anti-inflammatory medicines (NSAIDs) | Reduce pain and swelling around nerves | Can cause stomach, kidney or heart problems; ask your doctor first |
| Activity changes | Flexed positions, cycling, walking with support, short breaks | Simple and low-risk |
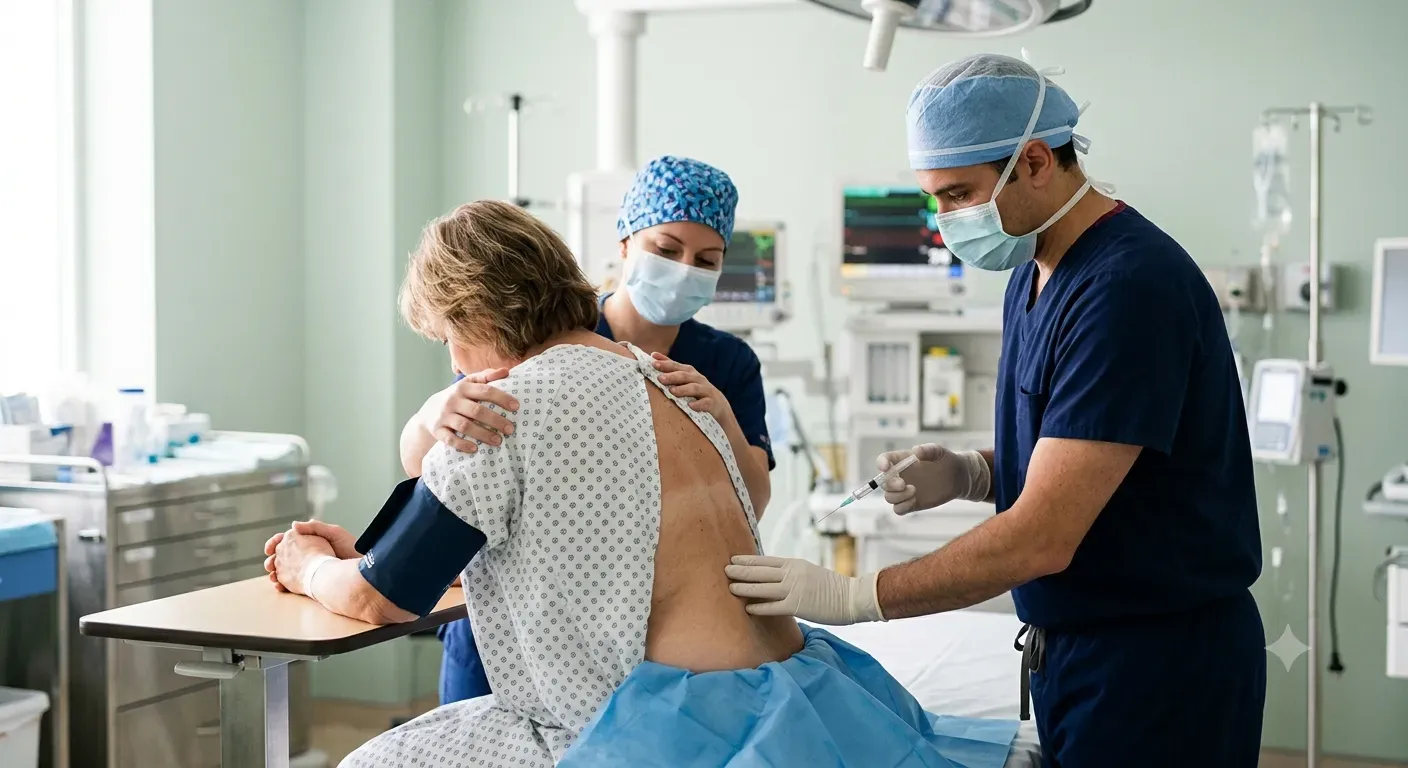
| Epidural steroid injections | Calm inflamed nerves to ease leg pain | Results vary; usually limited to about 3 a year |
| Spinal cord stimulation | Changes pain signals before they reach the brain | For selected people with long-lasting leg or back pain, often after other treatments; starts with a trial |
Do epidural injections work for stenosis?
They help some people, but the evidence is mixed. A large U.S. trial of 400 patients found that steroid-plus-numbing injections gave little or no extra benefit at 6 weeks compared with numbing medicine alone, though both groups improved. Injections tend to help leg pain and numbness more than weakness. Your doctor should talk with you honestly about whether an injection is likely to help in your case.
Is surgery better than physical therapy?
Not always. In a trial of 169 adults aged 50 and older who were candidates for surgery, physical function improved by similar amounts at 2 years whether they had decompression surgery or physical therapy. More than half of the physical therapy group later chose surgery, so it is a personal decision. A Cochrane review of 5 trials also found no clear winner.
Surgery (usually a laminectomy, sometimes with fusion) is generally considered when pain and weakness make walking very hard, when weakness is getting worse, or when nonsurgical care hasn’t helped enough.
Get emergency care if you suddenly have numbness in the groin or inner thighs, lose control of your bladder or bowels, or develop rapidly worsening leg weakness. These can be signs of cauda equina syndrome, which needs surgery right away.
Can I prevent stenosis from getting worse?
You can’t reverse the narrowing, but you can protect function: stay active, keep a healthy weight, strengthen your core, don’t smoke, and avoid long periods of standing still. Regular walking with rest breaks, cycling and water exercise are usually well tolerated.
How Wake Spine & Pain can help
Our board-certified pain physicians diagnose spinal stenosis with a hands-on exam, review of your imaging and, when needed, EMG and nerve conduction testing. Treatment plans can include physical therapy, epidural steroid injections and spinal cord stimulation, and we refer to spine surgeons when surgery is the better choice. Visit one of our clinics in Raleigh, Cary, Garner, Wake Forest, Fayetteville or Greenville, or call or text (919) 322-1835.
Spinal Stenosis FAQs
Can spinal stenosis be treated without surgery?
Yes. Most mild to moderate cases improve with physical therapy, anti-inflammatory medicines, activity changes, and epidural steroid injections.
Why does leaning forward relieve spinal stenosis pain?
Leaning forward widens the spinal canal and nerve openings, easing pressure on the nerves. Standing upright narrows them, which worsens symptoms.
Do epidural injections work for spinal stenosis?
They can ease leg pain and numbness for weeks to months by reducing nerve inflammation, but they don’t widen the canal, so relief is temporary.
Is physical therapy as good as surgery for spinal stenosis?
For many people with mild to moderate symptoms, long-term results are similar. Surgery may work better for severe symptoms or when therapy fails.
When is spinal stenosis an emergency?
Get urgent care for sudden bladder or bowel control loss, groin or inner thigh numbness, or rapidly worsening leg weakness. These can signal cauda equina syndrome.
References
- National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIH). Spinal Stenosis.
- American Academy of Orthopaedic Surgeons, OrthoInfo. Lumbar Spinal Stenosis.
- Delitto A, et al. Surgery versus nonsurgical treatment of lumbar spinal stenosis: a randomized trial. Ann Intern Med. 2015;162(7):465-473.
- Friedly JL, et al. A randomized trial of epidural glucocorticoid injections for spinal stenosis. N Engl J Med. 2014;371(1):11-21. doi:10.1056/NEJMoa1313265.
- Zaina F, et al. Surgical versus non-surgical treatment for lumbar spinal stenosis. Cochrane Database Syst Rev. 2016;(1):CD010264.
Related Posts



Last updated October 19, 2026